
Perioperative Warming
Hypothermia is a common complication under anesthesia that has many negative, if sometimes subtle, side effects for our patients. In the extreme it can cause cardiac arrest as the patient approaches 70° F, but in the more applicable examples hypothermia leads to increased risk of infection, relative anesthetic overdose (inhalant MAC decreases with hypothermia), impaired coagulation, delayed recovery from anesthesia, and shivering which is uncomfortable for the patient.
In humans, hypothermia is defined as core temperature below 35 C (95 F). Cooling of the patient happens initially during anesthetic induction through vasodilation and shunting of core blood to the periphery. Humans can lose about 2 C during anesthetic induction alone. Care must be taken using human examples as veterinary patients run the gamut of body surface to mass ratio with our smallest mammalian species being prone to hypothermia and our largest species maintaining relative euthermia or approaching hyperthermia. Heat loss through anesthetic induction is exacerbated when using agents that cause vasodilation, including acepromazine, propofol, and isoflurane, to name a few. Further heat loss occurs through radiation to the environment (often because the OR is set to a lower temperature to accommodate the surgeon), conduction through loss from the body to cold surfaces such as the metal operating table, evaporation, both through cold gas entering the trachea and loss through open body cavities, and finally through convection, the movement of air over a surface such as the intermittent blowing of the air conditioning. With the knowledge of the laws of heat transference, we can discuss how to appropriately warm our patients to minimize heat loss and combat these forces.
Commonly used methods of active warming include, a water blanket, a forced air warmer (such as a BAIR hugger), and a resistive polymer electric heating (HotDog Patient Warming System). Often two of these methods are employed at the same time to minimize heat loss to the environment (convection & radiation) and to the surfaces our patients come into contact with (conduction). We will start the discussion with the method that is most effective, and finish with options that will help and easy to do in under resourced environment. Forced air warmers are considered the safest and most effective way to non-invasively warm a patient while under anesthesia. These devices utilize warm air to provide a favorable gradient moving heat from the warmed blanket into the relatively colder patient, creating a kind of warm shell around the patient. It is important to utilize a device that was designed for this kind of activity and to use blankets designed for use with these systems. Makeshift blankets (e.g., wrapping the hose in a towel) can be problematic as the air temperature may not be even, and if providing warmed air via another system, such as a hair dryer, may result in an overly warm temperature that can cause burns. Warm water blankets and resistive polymer electric heating keep an increased temperature underneath the patient which works to reduce loss through conduction into the cold surface the patient is laying on. Additional methods that can be employed include wrapping the limbs and extremities to provide insulation, anecdotally bubble wrap has been used, while a 2022 using wool socks, and thermal blanket material (O’Neil 2022) showed that it can be effective at reducing heat loss during anesthesia. If these more expensive options are not available there is some hope that more passive and easily accessible options will help to reduce heat loss in our patients.


Other methods to control heat loss that bear mentioning would include pharmacologic methods: drugs that cause vasoconstriction maybe somewhat protective to heat loss. This would include alpha 2 agonists, (dexmedetomidine or xylazine). These drugs are commonly used in veterinary anesthesia but the vasoconstriction is dose dependent and when used as an adjunct to anesthesia we may not achieve these benefits. Once heat is lost in these patients the vasoconstriction may actually pose a limitation to patient warming. Fluid warmers can be effective at reducing heat loss from cold fluids, but the volume of fluids infused under anesthesia is often a small fraction of body weight and will have minimal effect. The rate of fluid administration may play a role in whether the fluids provide any heat support, and the fluid warmer placement is important to consider: further from the patient IV catheter will lead to loss of heat during transit.
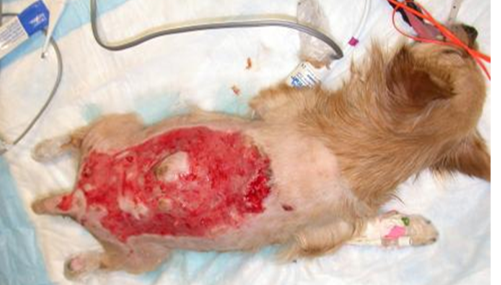
Anesthetized patients are also prone to thermal injury and supplemental heat methods need to be considered before being applied. Warming disks, socks filled with grains, electric blankets, microwaved fluid bags, and other such methods pose a risk to cause burns to patients under anesthesia. The anesthetized patient has abnormal blood flow and is unable to move away from the hot items, all of these factors make a burn more likely to happen when these forms of heat support are applied to the patient.

So with all of these things consider how do we provide perioperative heat support? Let’s take a case from the beginning to provide examples of where and how to provide heat support. Providing preoperative warming can be considered but may be limited in terms of effective due to time limitations and patient compliance issues. But once we have assessed the patient and are considering premedication, ensure that all methods of heat support are in place, and for some (warm water blankets) they are turned on to provide a stable temperature when the patient arrives. Once our patient is premedicated the clock is ticking, many of our premeds will alter patient thermoregulation, so giving premeds and preparing for a timely induction is integral. During induction we want to work to minimize heat loss, ideally we have a water blanket with or without a thin covering layer for the patient to rest on during induction and prep. A special note for cats to place the water blanket after induction as claws can easily pierce the blanket. Minimizing anesthetic time in one of the largest factors that could influence patient body temperature. Working to reduce prep is important, consider multitasking or utilizing multiple staff members to help instrument and prep patients if necessary, having supplies such a catheters andlocoregional supplies ready to minimize unnecessary delays. Once the patient is prepped and moved to the operating room, again reducing delays is imperative, have the surgeons been notified the patient is moving or is scrubbed? A common practice is to have a water blanket with a thin layer over it between the patient and the table surface or between the patient positioning device. Other under body options include a HotDog patient warming system or some forced air warmers provide underbody blankets, though these appear to work best on small patients. Covering as much of the patient as possible with a forced air warmer is best though this is easier in a dentistry or orthopedic type case and may not so easy when the abdomen is open. Using plastic sticky drapes that often come with the forced air warmer blankets can be used to help insulate the unexposed areas of the abdomen. Additionally other passive methods may be used at this time, wool socks on extremities, reflective blanket coverings.
Once the surgery is complete and if the patient is hypothermic, providing heat support throughout the recovery process is integral to helping to return the patient to homeostasis. Thorough temperature monitoring should be utilized during the perioperative period including recovery. Heat support should be removed once the patient is euthermic, though overly sedate patients in recovery may still benefit from heat support until up and moving around. All of these methods work best if they are easily accessible and commonplace in your practice. Delaying the procedure to get supplies can exacerbate heat loss so consider what is practical and available to your practice.
O’Neil, B. A., & Linklater, A. K. (2022). Supplemental reflective blankets and wool socks help maintain body temperature in dogs undergoing celiotomy procedures: a prospective randomized controlled clinical trial. Journal of the American Veterinary Medical Association, 1(aop), 1-8.


Trước đây mình từng thấy vào good88 com vài lần nhưng gần đây mới có thời gian ấn vào xem kỹ hơn một chút. Mình chủ yếu quan sát bố cục địa phương và cách các phần thông tin được đặt trên trang. Tổng thể khá thoáng nên việc xác định từng khu vực không bị mất nhiều thời gian, thao tác chuyển mục cũng phản hồi nhanh. Mình chưa sử dụng lâu nên muốn hỏi thêm các bác đã theo dõi thường xuyên trải nghiệm thực tế thế nào.
Trong lúc tìm kiếm thông tin về các website giải trí trực tuyến, mình phát hiện nhà cái MU88 xuất hiện trong khá nhiều bài đánh giá nên tiện tay vào xem thử. Sau khi trải nghiệm sơ bộ, mình nhận thấy giao diện được thiết kế đơn giản nhờ áp dụng bố cục hợp lý giúp phân định rõ khu thể thao với live casino nên khá dễ theo dõi. Cách phân loại các trò chơi slot thông minh vào từng sảnh game hỗ trợ trang tải tương đối nhanh và những thao tác cơ bản diễn ra mượt mà. Dù vậy, mình vẫn muốn tham khảo thêm trải nghiệm thực tế từ cộng đồng để có cái nhìn đầy…
Trong quá trình tham khảo một số website giải trí trực tuyến, mình tình cờ bắt gặp 789 p qua một nội dung được chia sẻ trên mạng. Vì chưa biết nhiều về trang này nên mình truy cập thử, chủ yếu quan sát giao diện và cách sắp xếp các chuyên mục game bài, xóc đĩa, tài xỉu... Ấn tượng đầu tiên là phần trình bày khá đơn giản, từng khu vực được bố trí tương đối rõ nên khi lướt nhanh vẫn dễ nhận biết nội dung. Mình cũng thử chuyển qua vài mục khác nhau và thấy trang phản hồi khá nhanh, các thao tác cơ bản thực hiện tương đối thuận tiện. Nhìn chung trải nghiệm ban…
The landing page keeps things minimal and the navigation is easy to scan, so it works well as a quick starting point for browsing entries. If you want to see how the site is organized, the collaborative wiki homepage lays it out plainly.
Có chút tò mò sau khi đọc qua vài bài review về tk888 mình ghé website để xem thực tế. Mình chủ yếu quan tâm đến cách trình bày giao diện. Chỉ lướt nhanh tổng thể nên chưa tìm hiểu sâu, nhưng ấn tượng ban đầu là bố cục khá rõ ràng, các phần được chia hợp lý nên nhìn không bị rối mắt. Nội dung hiển thị gọn gàng, dễ theo dõi, thanh menu đặt ở vị trí dễ thấy nên việc chuyển qua lại giữa các mục cũng khá nhanh. Khi truy cập bằng điện thoại, trang vẫn hoạt động ổn định, thao tác mượt. Tổng thể mang cảm giác đơn giản, dễ dùng